

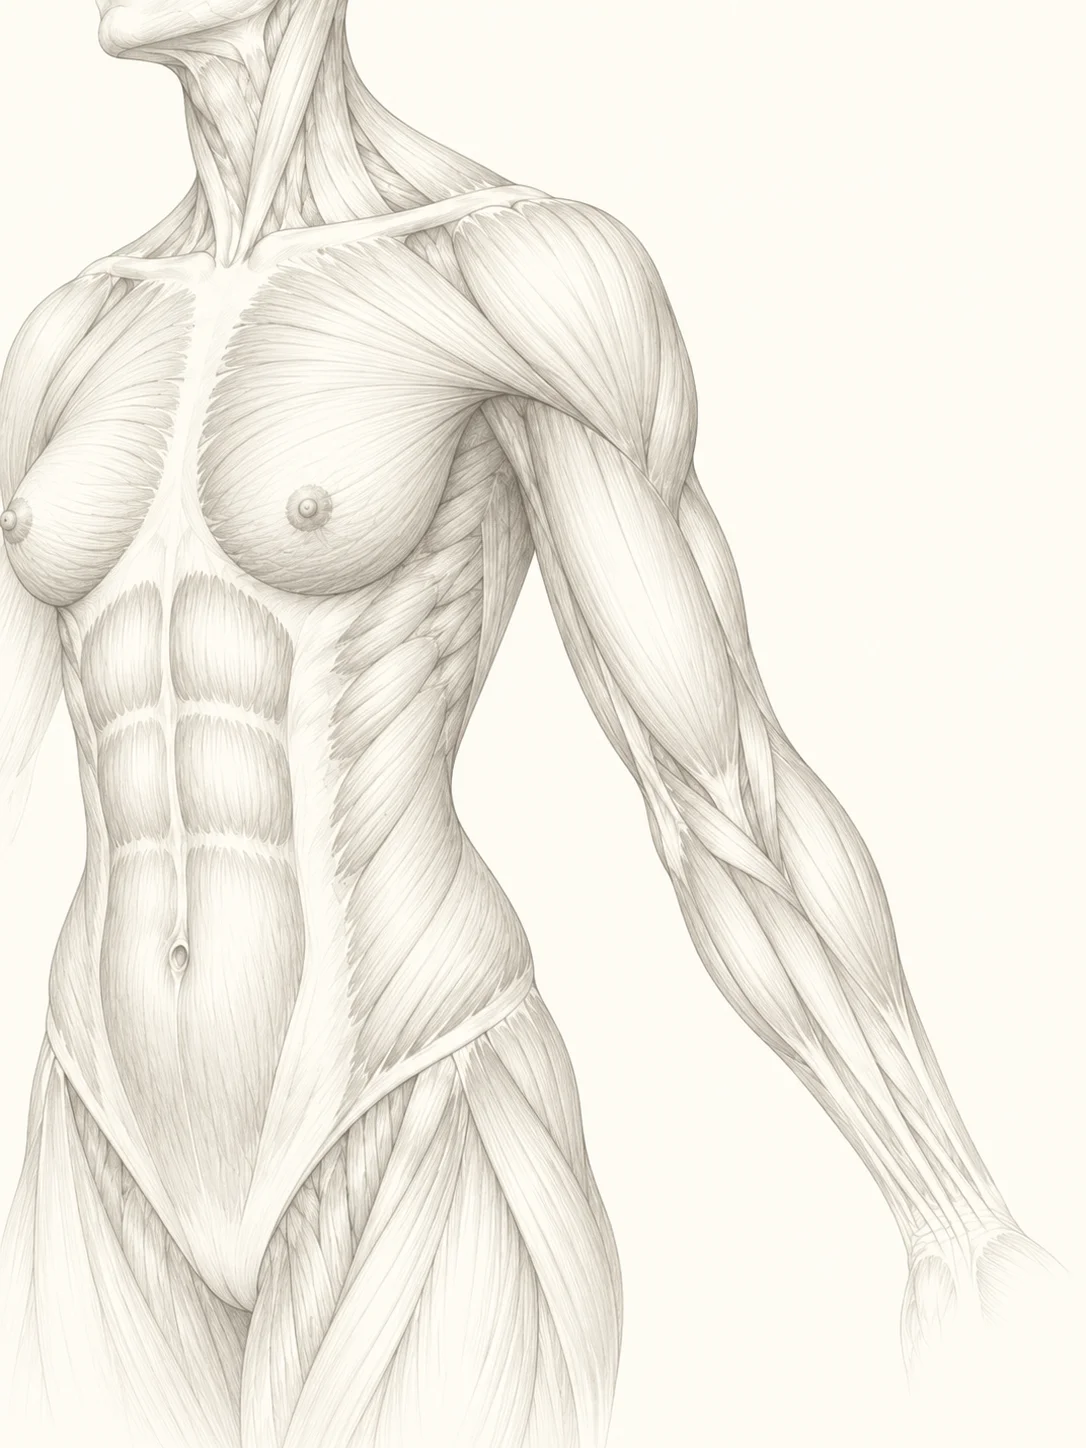
The problem this operation is actually built to solve
Most people think of a tummy tuck as horizontal skin removal, and for most abdomens that is the correct model. The excess sits low, it is removed through a low transverse excision, and the abdomen flattens. After major weight loss the anatomy is frequently different. The redundancy is three-dimensional: there is excess skin in height and excess skin in width, and the two do not respond to the same manoeuvre.
In that anatomy a standard abdominoplasty can leave persistent central looseness. The patient reaches a stable weight, does everything correctly, and is still left with a loose central abdomen that exercise does not change and clothing does not accommodate predictably. The fleur-de-lis design exists specifically to address that pattern.
What a fleur-de-lis abdominoplasty actually is
A fleur-de-lis abdominoplasty is a tummy tuck technique that removes excess skin through two excisions rather than one: a horizontal excision low on the abdomen, and a vertical excision in the midline. That combination allows the abdomen to be tightened in two directions instead of one. Muscle repair may be included when diastasis is present and is contributing to the contour or to function.
It is most commonly used after massive weight loss, where significant central abdominal redundancy is the defining feature. It is not a more aggressive tummy tuck offered to everyone who wants a stronger result. It is a specific solution to a specific redundancy pattern.
The vertical scar is the price of the second direction.
There is no way to remove central width without a midline excision, and there is no way to make a midline excision without a vertical scar. That is the entire trade-off, stated plainly. If a patient has significant vertical redundancy, the scar may be the only route to a coherent contour. If they do not, the scar is not justified — and adding it would mean accepting a permanent cost for a marginal gain.
How anatomy decides whether this is the right operation
Candidate selection is the operation. The examination question is not how much skin there is but in which directions it is redundant, because that determines whether one excision or two is required. A patient with lower abdominal excess and a reasonable central contour has no reason to accept a vertical scar. A patient whose abdomen falls loosely inward at the midline will not be adequately corrected by a horizontal excision alone.
Weight stability matters, as does overall health, prior abdominal scarring, and scar tolerance. Prior scars in particular can affect blood supply and change the plan, sometimes substantially.
Tension and blood supply govern the closure
Tightening in two directions increases the complexity of the closure. Where two excisions meet, tension and vascularity have to be managed together rather than separately, and conservative planning at that point is what reduces wound-healing risk. Individual tissue behaviour then influences scar quality, swelling and how quickly the contour becomes stable.
Which redundancy pattern do you actually have?
The comparison below is not a ranking of techniques. It describes how three different presentations lead to three different recommendations, one of which involves accepting a scar the others do not.
The pattern of excess determines the design
| Feature | Lower abdominal excess only | Vertical and horizontal excess | Minimal laxity, fat-dominant |
|---|---|---|---|
| Typical background | Post-pregnancy or moderate weight change | Major or massive weight loss | Stable weight, localised fullness |
| Appropriate design | Horizontal excision alone | Horizontal plus vertical excision | Contouring rather than excision |
| Scar consequence | Low transverse scar | Low transverse scar plus a midline vertical scar | Small entry points |
| What happens if the wrong design is chosen | An unnecessary vertical scar | Persistent central looseness | Skin removal for a problem that was not skin |
What happens conceptually during surgery
Excess skin is removed in two planes. A low horizontal excision addresses height, and a midline vertical excision addresses width, allowing the abdominal wall to be re-draped in both directions. Where diastasis is present and relevant, muscle repair is included — but that decision is anatomy-led rather than automatic.
The governing discipline throughout is tension management. Two-direction tightening is more demanding to close than a single excision, and the conservative choice at closure is what protects healing. In selected cases liposuction can be combined, but combinations must remain conservative to protect blood supply.
Scars are planned for stability, not for invisibility
I place and design scars to heal reliably rather than to be concealed at all costs, because a scar that heals badly in a hidden position is a worse outcome than a scar that heals well in a visible one. This operation is not scar-free, and it is not marketed as such. The patient who does the best with it is the one who has understood and accepted the scar before surgery rather than been reassured about it.
What it can change, and what it cannot
It can achieve improved central tightening and waist definition in a way standard techniques cannot, restoring a flatter abdomen and a narrower waist. What it cannot do is act as a weight-loss procedure, guarantee a perfectly flat abdomen in all postures, or eliminate scarring. And it is not the right answer when vertical redundancy is minimal, or when the patient cannot accept a vertical scar — in which case the honest recommendation is a different operation, or none.
I will not add a scar to justify a bigger operation
When a patient asks for the strongest possible abdominal result, my answer depends entirely on what the examination shows. If the vertical component is not there, I will recommend the horizontal design and explain why the additional scar would be a cost without a corresponding benefit. Choosing the smaller operation when it is sufficient is part of the surgical judgement, not a lack of ambition.
Recovery is a sequence, not a single date.
- Early phaseTightness and swelling
Tightness and swelling are expected after two-direction tightening. Wound healing is monitored closely during this period, and it is the phase in which the closure is most demanding.
- Staged activity returnProgressive, not immediate
Activity is returned to in stages rather than at a single point. The pace is set by how the closure is healing rather than by a schedule.
- Scar maturation phaseMonths
Scars mature over months, and both scars change considerably during that time. The contour becomes stable over the same horizon.
Recovery variability should be expected. I avoid fixed timelines because healing depends on surgical scope and individual tissue behaviour.
What should be weighed in the decision?
This is an operation where the central trade-off is unusually clear, and it should be understood before consent rather than after.
- Trade-off: a vertical midline scar is accepted in exchange for tightening in a second direction.
- Trade-off: the low transverse scar remains in addition to the vertical one; this design adds a scar rather than replacing one.
- Trade-off: two-direction tightening increases closure complexity and therefore wound-healing risk.
- Trade-off: activity return is staged, which has real consequences for work, travel and family responsibilities.
- Trade-off: combining with liposuction can improve the overall result but must be restrained to protect blood supply.
- Limitation: wound-healing problems and scarring issues are recognised risks.
- Limitation: seroma is a recognised risk of this design.
- Limitation: contour irregularity can occur.
- Limitation: the abdomen will not be perfectly flat in all postures.
- Limitation: it is not scar-free, and no honest plan describes it as such.
- Limitation: it is not a weight-loss procedure.
- Limitation: individual tissue behaviour influences scar quality, and that is not fully predictable in advance.
- Limitation: prior abdominal scars can affect blood supply and constrain the plan.
- Limitation: muscle repair is only appropriate where diastasis is genuinely present and contributing.
- Limitation: each revision increases scar burden and reduces predictability.
- Limitation: ageing and weight change continue to affect the tissues afterwards.
- Alternative: a standard abdominoplasty, when the excess is mainly in the lower abdomen.
- Alternative: contouring rather than excision, when laxity is minimal and fat is the dominant component.
- Alternative: waiting until weight is genuinely stable, when it is not yet.
- Alternative: declining surgery, which is the correct outcome when the vertical scar cannot be accepted.
How to think about the decision
Two questions are worth asking directly. First: is my redundancy genuinely vertical as well as horizontal, and what specifically on examination shows that? Second: if I had the horizontal design alone, what would be left uncorrected?
If the answer to the second question is “very little”, the vertical scar is not worth accepting. If the answer describes exactly the looseness that has been bothering you, then the trade-off is a rational one. When properly indicated, this operation restores abdominal contour in a way standard techniques cannot. The best outcomes come from correct indication, conservative tension management and disciplined aftercare.
Am I a good candidate for fleur-de-lis abdominoplasty?
Good candidates typically have significant vertical and horizontal skin redundancy, often after major weight loss, and a stable weight. I assess redundancy pattern, scar tolerance and overall health. A good candidate accepts the vertical scar trade-off and understands that individual tissue behaviour influences scarring.
Why is the vertical scar necessary?
Because it allows tightening in the horizontal dimension and removal of central excess that a horizontal-only excision cannot address.
Will I still have a lower tummy tuck scar?
Yes. This design includes the standard low scar plus an additional vertical scar.
Is this just a stronger version of a standard tummy tuck?
No. It is a different design for a different redundancy pattern. It is not a more aggressive option offered to anyone who wants a bigger change.
When is fleur-de-lis not the right answer?
When vertical redundancy is minimal, or when the patient cannot accept a vertical scar.
How variable is recovery?
Swelling, tightness and wound healing vary. I avoid fixed timelines because healing depends on surgical scope and individual tissue behaviour.
What are the main risks?
Wound-healing problems, scarring issues, seroma and contour irregularity. Conservative planning reduces risk.
Do I need muscle repair as well?
Only if diastasis is present and contributes to contour or function issues. The decision is anatomy-led.
Can it be combined with liposuction?
In selected cases, yes, but combinations must be conservative to protect blood supply.
What if I have prior abdominal scars?
Prior scars can affect blood supply and planning. The plan is individualised accordingly.
Can the scars be improved later?
Scar refinement or contour adjustment can be considered after full healing, but each revision increases scar burden and reduces predictability.
How long-lasting are results?
Results can be durable with weight stability, but ageing and weight changes still affect tissues. A conservative plan tends to age more naturally.



