

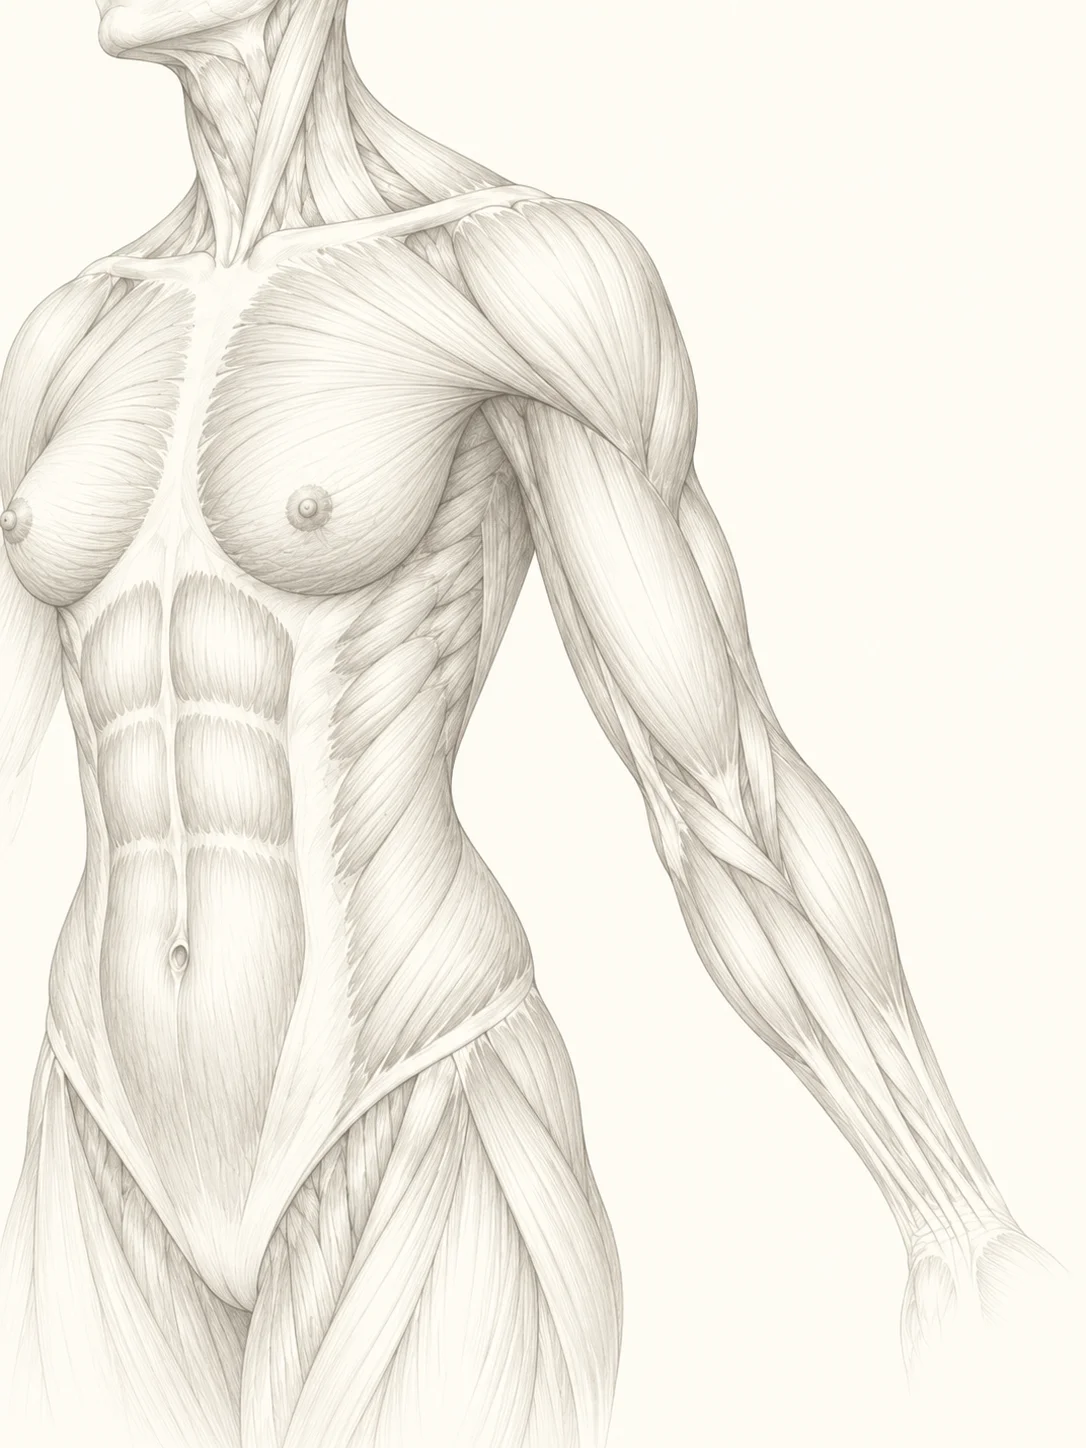
Body contouring is usually reduced to liposuction. That reduction is the reason a large share of patients end up dissatisfied, because it collapses a planning problem into a single tool.
Body contouring is an umbrella term covering different techniques, each with specific indications and limitations. The outcome is not decided by how aggressively fat is removed. It is decided by whether the method matches the anatomy — fat distribution, skin elasticity, and the structural framework beneath.
What the category actually contains
Body contouring refers to surgical and, in selected cases, non-surgical procedures designed to improve body shape by reducing localised fat, tightening or excising excess skin, and restoring smoother transitions between regions.
That includes liposuction-based contouring, skin excision procedures such as abdominoplasty and body lifts, and combination approaches. It is most appropriate when someone is near a stable weight but has disproportionate areas that do not respond well to training, nutrition, or time.
Fat is not the same as laxity
Many patients describe fat when the dominant issue is actually skin redundancy or weakened support. Liposuction can reduce thickness, but it does not reliably tighten skin beyond the skin’s own recoil capacity. If the envelope is poor, removing volume can reveal laxity more clearly, creating a softer or even irregular surface. Excision-based procedures can tighten the envelope, but they do it by trading laxity for scars. A responsible plan is one that acknowledges which trade-off is acceptable and which is not.
The body is defined by transitions, not by zones
The abdomen blends into the flanks. The waist blends into the lower back. The outer thigh blends into the hip. The upper arm blends into the axilla and lateral chest.
A proportional map, not a spot-treatment mindset
If one zone is treated in isolation, the result can look disconnected. I plan areas based on those shared borders — treating the abdomen without considering flanks and lower back can leave a contour break, and treating the outer thigh without considering hip transitions can create an unnatural edge. The goal is not to treat every area. It is to treat the regions that define the silhouette and to blend them conservatively.
Which pattern is dominant decides the tool
Matching the method to the anatomy is the entire decision. Treating body contouring as liposuction for everyone is a common reason patients end up dissatisfied.
Fat-dominant, envelope-dominant, and mixed anatomy
| Feature | Fat-dominant with good skin | Envelope-dominant with significant laxity | Mixed pattern |
|---|---|---|---|
| The dominant driver | Localised fat thickness, with sufficient skin elasticity | Skin redundancy or weakened support rather than volume | Both a volume component and a compromised envelope |
| Method that fits the mechanism | Liposuction-based contouring is the right tool | Skin excision procedures such as abdominoplasty or body lifts | A combined approach, often better staged than compressed |
| What happens if the method is mismatched | Extensive excision may be unnecessary when fat is modest and skin is good | Liposuction alone may under-deliver, or reveal laxity more clearly | Treating only one component leaves the other visible |
| The currency of the trade-off | Irregularity and waviness if reduction exceeds what the surface tolerates | Longer scars, wound healing variability, changes in sensation | More regions healing at different rates, and more patience required |
Volume reduction is also internal tissue trauma
Liposuction is not only subtraction. Too much aspiration, poor blending, or aggressive superficial work can create waviness, firmness, or a surface that looks thin and unnatural.
Skin excision procedures carry their own profile: longer scars, wound healing variability, and changes in sensation. In both categories, individual tissue behaviour influences swelling, scar maturation and long-term stability — particularly in post-weight-loss skin and in areas with less elasticity.
More areas is not a more complete plan
Combining many regions increases operative time, swelling and recovery complexity, so the plan has to balance aesthetic coherence against physiologic limits. That means the question is never how much can be treated, but which regions genuinely define the silhouette and how conservatively they can be blended into each other. Adding areas to feel thorough moves the plan away from a good result rather than toward one.
What body contouring is not
It is not a weight loss strategy. It does not replace lifestyle, and it does not change the underlying metabolic tendencies that lead to weight gain.
It is not a method to create a guaranteed athletic definition, because definition depends on muscle, skin thickness and natural anatomy. And it is not a promise of symmetry — baseline asymmetry in pelvis, rib cage and posture is normal and persists.
When it is not the right answer
If weight is still fluctuating, the body is still changing and the contour result is less stable. If someone expects a dramatic change without scars but the anatomy requires skin excision for meaningful improvement, the expectation and the anatomy are misaligned. If skin is very lax and the patient insists on liposuction only, the likely outcome is disappointment.
The mismatch also runs the other way: where the fat component is modest and the skin is good, extensive excision may be unnecessary. And where medical risk factors make wound healing or anaesthesia risk unacceptable, the correct choice is to do less, to stage, or to do nothing when the trade-off is not fair.
Skin quality is usually the real ceiling
In many patients, the limiting factor is not fat but skin. Fat can be reduced. Skin recoil cannot be manufactured beyond what the tissue can do. If the skin is thin, stretched, or significantly lax, aggressive liposuction can lead to irregularity or persistent looseness. If meaningful tightening requires excision, scars become part of the trade-off. A responsible plan makes this limitation explicit early rather than discovering it afterwards.
Staging is not less treatment
When multiple regions need attention or skin quality is poor, staging is often the safer approach. It reduces operative time, allows clearer healing feedback, lowers the risk of overcorrection, and permits more precise adjustment based on how the tissues actually settle. For many patients, staging is a more controlled path to a stable result rather than a compromise. The same logic governs the amount: a conservative result often ages better, because it avoids overly thinned areas and preserves natural transitions. The goal is a quieter silhouette, not maximal change.
Recovery depends on which technique was used
Liposuction recovery is often dominated by swelling, bruising and firmness that gradually softens. Excision procedures add scar management and longer tissue settling. Combination procedures require more patience, because multiple regions heal at different rates.
Recovery is a sequence, not a single date.
-
Early phase
Early contour is not final contour
Swelling is not uniform, so the surface can look uneven. The area often feels tight or temporarily numb. Compression supports swelling control and re-draping, but it cannot replace skin elasticity.
-
Settling phase
The contour becomes clearer in phases over weeks to months
Firmness softens and tissues relax. Where excision was involved, scar firmness can fluctuate and the scar continues evolving for months according to tension, skin type and aftercare.
-
Assessment phase
The result is read once the body has settled
I avoid fixed timelines, because recovery is individualised and the settling process is gradual. In post-weight-loss tissue, healing can be slower.
What should be weighed in the decision?
Every route through body contouring spends something. Reduction spends surface smoothness; excision spends scars. The decision is which currency is acceptable for your anatomy.
- Trade-off: excision tightens the envelope by trading laxity for scars. Scar appearance depends on tension, skin type and aftercare, and it evolves for months.
- Trade-off: where skin is poor, removing volume can reveal laxity more clearly rather than resolving it.
- Limitation: with liposuction, the main aesthetic risks are irregularity, waviness and contour breaks where transitions are not blended. Fluid collection and prolonged firmness can occur.
- Limitation: with excision, wound healing issues, scar widening and changes in sensation are more relevant. In post-weight-loss tissue, healing can be slower.
- Limitation: asymmetry can persist, because baseline asymmetry in pelvis, rib cage and posture is normal and healing variability is real.
- Limitation: athletic definition cannot be guaranteed, because it depends on muscle, skin thickness and natural anatomy.
- Limitation: combining many areas increases operative time, swelling and recovery complexity. Aesthetic coherence has to be balanced against physiologic limits.
- Limitation: results can be durable when weight is stable, but ageing continues, skin elasticity changes, and weight fluctuations can alter contour over time.
- Limitation: each revision increases scar burden and uncertainty. Any revision should be conservative and only after tissues have stabilised.
- Alternative: where the concern is primarily excess weight rather than contour, medical weight optimisation is usually the more appropriate first step.
- Alternative: staging is often safer than compressing multiple regions into one session.
- Alternative: doing less, or doing nothing, is the correct decision when the trade-off is not fair or when medical risk factors make healing or anaesthesia risk unacceptable.
If you have had contouring before and want further refinement
Secondary contouring requires restraint, because tissue planes are altered and scar burden increases.
The first task is determining whether the concern is residual fat, scar tissue firmness, or an envelope problem that liposuction cannot solve. In some cases the correct next step is not more liposuction, but addressing skin laxity — or accepting that the tissue ceiling has been reached. Where revision is considered, it should be targeted and conservative, and only after the prior result has fully matured.
How long-lasting the result is
Results can be durable when weight is stable and the plan respects tissue mechanics. But ageing continues, skin elasticity changes, and weight fluctuations can alter contour over time.
The honest framing is a proportional reset, not a permanent freeze of biology. When properly indicated, body contouring delivers a quieter silhouette: improved waist definition, reduced focal fullness, and smoother regional transitions. The best results come from careful anatomic assessment, conservative technique selection, and planning that prioritises long-term stability over aggressive short-term change.
Am I a candidate for body contouring, or do I need to lose weight first?
Body contouring is most predictable when weight is stable and close to a sustainable baseline. If someone is still actively losing weight, the skin envelope and fat distribution are still changing, which makes planning less stable. In consultation, I assess BMI, weight trend, and whether the main concern is disproportionate fat pockets or loose skin. If the issue is primarily excess weight rather than contour, medical weight optimisation is usually the more appropriate first step. If weight is stable and the concern is localised contour imbalance, body contouring may be properly indicated. The goal is proportional refinement, not weight reduction.
Is body contouring just liposuction?
No. Liposuction is one tool, and it is the right tool when the dominant issue is localised fat thickness and the skin has sufficient elasticity. When skin laxity is dominant, liposuction alone may under-deliver or even reveal laxity more clearly. Body contouring also includes skin excision procedures such as abdominoplasty and body lifts, and sometimes a combined approach. The correct method depends on the anatomy: fat versus envelope. Treating body contouring as liposuction for everyone is a common reason patients end up dissatisfied.
How do you decide which areas to treat together?
I plan areas based on transitions. Treating the abdomen without considering flanks and lower back can leave a contour break. Treating the outer thigh without considering hip transitions can create an unnatural edge. The goal is not to treat every area. It is to treat the regions that define the silhouette and to blend them conservatively. Safety matters as well. Combining many areas increases operative time, swelling, and recovery complexity, so the plan must balance aesthetic coherence with physiologic limits.
What is the biggest limitation in body contouring?
In many patients, the limiting factor is skin quality. Fat can be reduced. Skin recoil cannot be manufactured beyond what the tissue can do. If the skin is thin, stretched, or has significant laxity, aggressive liposuction can lead to irregularity or persistent looseness. If meaningful tightening requires excision, scars become part of the trade-off. A responsible plan is the one that makes this limitation explicit early and sets realistic expectations about what can and cannot be achieved.
When is body contouring not the right answer?
It is not always the right answer when weight is unstable, when expectations are centred on dramatic transformation without scars, or when someone wants maximal reduction regardless of tissue limits. It can also be inappropriate when medical risk factors make wound healing or anaesthesia risk unacceptable. In some cases, the correct choice is to do less, to stage, or to do nothing when the trade-off is not fair.
How variable is recovery after liposuction-based contouring?
Swelling and firmness are normal, and the timeline is variable. Early contour can look uneven because swelling is not uniform. The area often feels tight or numb temporarily. Compression is commonly used to support swelling control and re-draping, but it cannot replace skin elasticity. The contour becomes clearer in phases over weeks to months. Individual tissue behaviour determines how quickly swelling resolves and how the surface softens.
How variable is recovery after skin excision procedures?
Excision procedures add another layer of recovery: scar maturation and wound healing variability. Tightness is expected early. Swelling can be prolonged, and scar firmness can fluctuate. The scar evolves for months, and its appearance depends on tension, skin type, and aftercare. In post-weight-loss tissue, healing can be slower. I avoid fixed timelines because recovery is individualised and because the body’s settling process is gradual.
What are the main risks I should understand?
With liposuction, the main aesthetic risks are irregularity, waviness, and contour breaks if transitions are not blended. Fluid collection and prolonged firmness can occur. With excision procedures, wound healing issues, scar widening, and changes in sensation are more relevant. Asymmetry can persist because baseline asymmetry and healing variability are real. The way to reduce risk is conservative planning, respecting tissue limits, and avoiding maximal approaches that exceed skin capacity.
What if I have had body contouring before and want further refinement?
Secondary contouring requires restraint because tissue planes are altered and scar burden increases. I first determine whether the concern is residual fat, scar tissue firmness, or an envelope problem that liposuction cannot solve. In some cases, the correct next step is not more liposuction, but addressing skin laxity or accepting that the tissue ceiling has been reached. If revision is considered, it should be targeted and conservative, and only after the prior result has fully matured.
How long-lasting are body contouring results?
Results can be durable when weight is stable and the plan respects tissue mechanics. However, ageing continues, skin elasticity changes, and weight fluctuations can alter contour over time. A conservative result often ages better because it avoids overly thinned areas and preserves natural transitions. I encourage patients to view body contouring as a proportional reset, not a permanent freeze of biology.
Can body contouring be staged, and why would that be preferable?
Yes, staging is often the safer approach when multiple regions require attention or when skin quality is poor. Staging reduces operative time, allows clearer healing feedback, and lowers the risk of overcorrection. It also allows more precise adjustment based on how the tissues settle. For many patients, staging is not less treatment. It is a more controlled path to a stable result.
Will body contouring give me athletic definition?
Not as a guarantee. Definition depends on muscle, skin thickness, and natural anatomy, not only on how much fat is reduced. Contouring can improve waist definition, reduce focal fullness, and smooth regional transitions, but it cannot manufacture a level of definition the underlying anatomy does not support. Pursuing that with aggressive superficial work risks waviness and a surface that looks thin and unnatural.



