

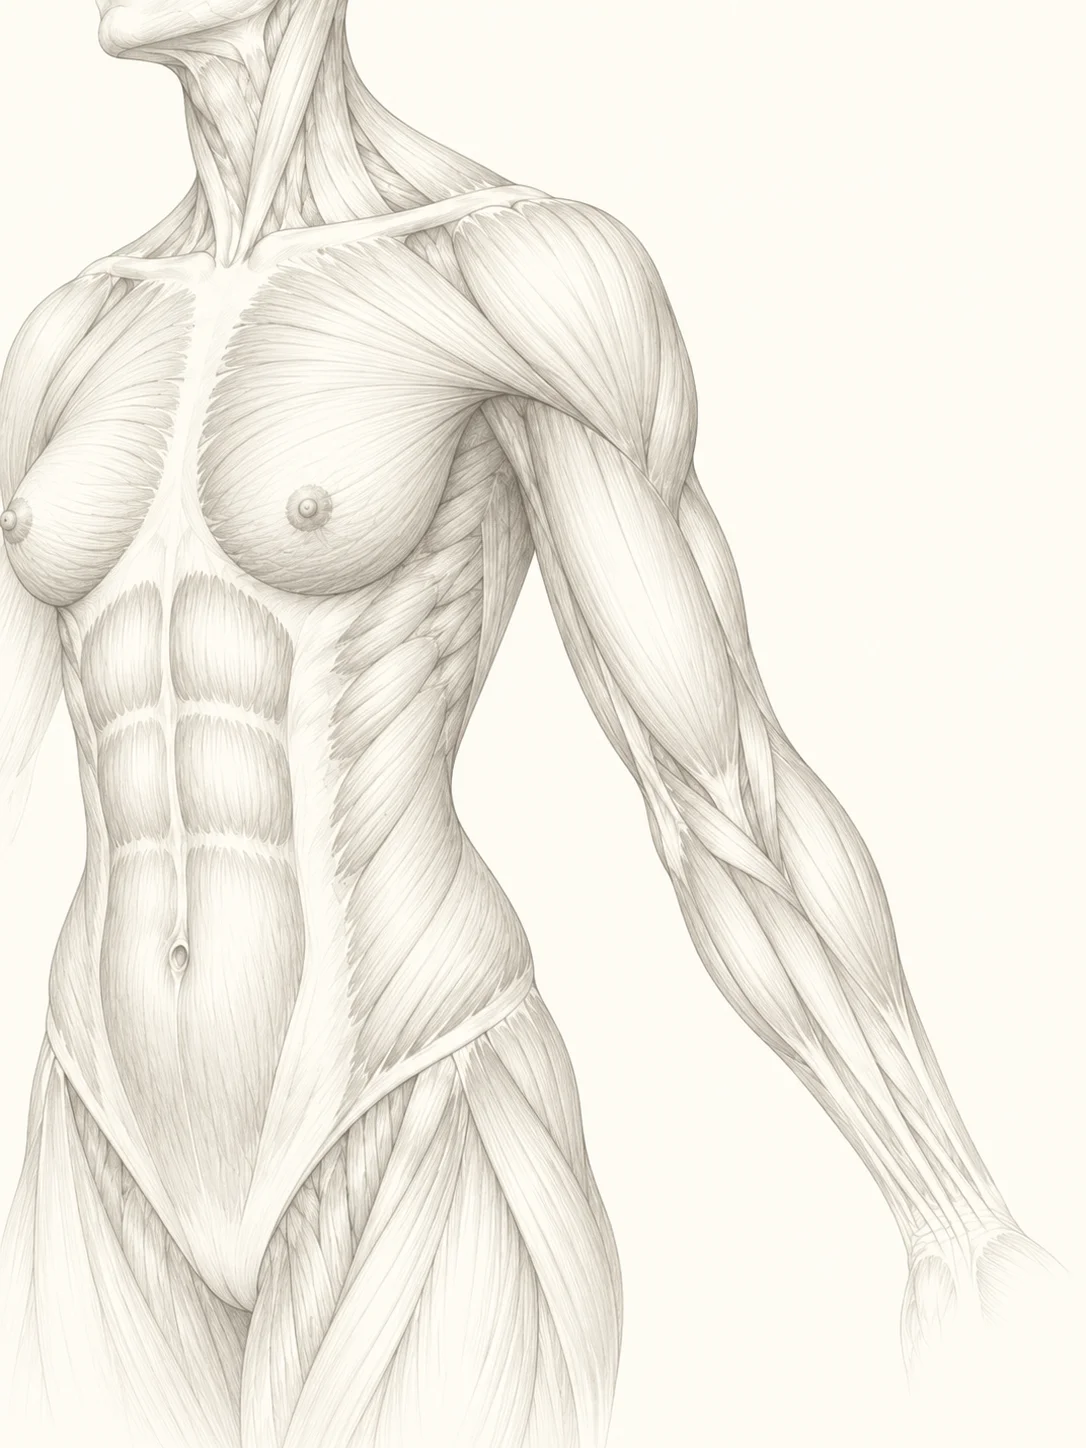
Most people describe the goal as slimmer arms. That sentence is not a diagnosis. The clinical question is more specific: would this arm look better with fat reduction, with skin removal, or with no surgery at all.
The common assumption is that those options are interchangeable. They are not. The dominant anatomical driver determines the correct tool, and the wrong tool can produce an arm that is smaller but less attractive, because the silhouette becomes less coherent. An arm lift is therefore less about slimming and more about managing the skin envelope — and skin removal carries a scar footprint that has to be planned, accepted and allowed to mature.
What an arm lift actually is
An arm lift, also called brachioplasty, is an excision-based procedure designed to treat true excess skin of the upper arm. The word that matters is skin. Excess skin is removed and the remaining envelope is re-draped to create a cleaner contour. In some patients liposuction is used as a supporting tool to manage volume, but it is not the identity of the operation. The identity is envelope control.
When properly indicated, this can reduce the hanging skin that makes sleeves uncomfortable and makes the arm look heavy even when weight is stable. What it cannot do is tighten an envelope without removing anything.
Classification comes before technique
Some arms look large primarily because of fat thickness. Some look heavy because the skin envelope has lost recoil and hangs or ripples with motion. Many people have a mixed pattern. The method changes depending on which factor is dominant, which is why I do not start with a technique name. I start with classification — fat-dominant, skin-dominant, or mixed — and only then ask what footprint is justified.
Liposuction or excision: an anatomical decision, not a preference
The key question is what is limiting the silhouette. If the arm looks heavy primarily because of fat thickness and the skin has reasonable recoil, liposuction can sometimes deliver a clean improvement. If the main limitation is skin laxity, liposuction does not reliably tighten the envelope — and removing fat from a lax arm can leave the same loose envelope with less internal support, so the arm can read as more lax than before.
Three patterns, three honest answers
| Feature | Fat-dominant | Skin-dominant | Mixed |
|---|---|---|---|
| What limits the silhouette | Fat thickness, with reasonable skin recoil | Loss of envelope recoil; skin hangs or ripples with motion | Both, in varying proportion |
| Reasonable approach | Liposuction can sometimes deliver a clean improvement | Excision — skin removal and re-draping | A conservative plan; aggressive contouring risks irregularity |
| Main risk of the wrong tool | Excision may cost more scar than the benefit is worth | Fat removal alone can make the arm look more lax | Over-treatment in either direction |
| Scar footprint | Limited | Proportionate to the extent of laxity | Decided by which driver is being treated |
Mixed patterns are common, particularly after weight changes and with age-related loss of recoil. The honest endpoint is not lipo versus lift. It is which driver dominates, and what footprint is justified for the benefit being sought.
Why the upper arm is more demanding than it looks
The anatomical complexity here is underestimated, because people see one fold and assume one solution. Arm contour is actually read in transitions: shoulder to upper arm, upper arm to elbow, and inner arm to axilla.
Contour is read at the transitions, not at one fold
A small irregularity in one segment can be more visible than a larger change elsewhere, particularly in side lighting and during movement. The arm also has relatively thin soft tissue in many patients, which makes the surface less forgiving when tension is excessive or contouring is aggressive. That geometry sets the discipline: design for transitions and for motion, not for a single posed angle.
The arm has to look normal when it moves
Over-tightening is the most common reason an arm lift looks operated. If tension is excessive the contour can look pulled, and scar tension increases, which can in turn worsen scar quality. Disproportion is the other cause: reducing the arms considerably while the torso is untreated creates a visual mismatch. A quiet result is usually the better result — it reads as normal anatomy rather than as an edited body.
The scar is the trade-off, not a footnote
This is not a scarless tightening procedure. If you want skin removal, you are accepting scars. That is not a warning; it is the core trade-off of the operation.
Scar placement can be planned to be as discreet as anatomy allows and tension can be managed, but visibility is heavily influenced by both. Where closure is under high tension, the risk of widening increases. Where skin is thin or fragile, scar behaviour is less predictable. Pigmentation tendencies vary across individuals and skin types. I can control incision placement and tension strategy; I cannot control scar biology by agreement. Scars usually mature and fade, but they do not become imaginary — and a good plan is one in which the trade-off is accepted in advance rather than hoped away.
The question of a short scar
A limited approach is sometimes possible, but only in a specific anatomy. The honest limitation is geography. If laxity extends along the inner arm toward the elbow, a very short scar cannot remove enough skin to change the silhouette meaningfully.
When a mini scar is requested within a larger laxity pattern, the result is usually one of two compromises: under-correction, or a scar under tension that heals poorly. The correct question is not how short the scar can be. It is what footprint is justified by the degree and location of laxity. Where laxity is mild and localised, a limited approach may be reasonable. Where it is more extensive, treating it as a limited problem is how surgery becomes dishonest.
The smallest footprint that honestly addresses the dominant driver
My philosophy here is consistent: choose the smallest footprint that honestly addresses the dominant driver, design the contour for motion and for transitions, respect scar biology, and set expectations from individual tissue behaviour rather than from a template. A premium plan is not maximum correction. It is a fair trade.
Who may reasonably be considered — and who should wait
The operation suits an arm where skin laxity is genuinely the limiting factor and where the improvement available is worth the scar footprint. In consultation I try to quantify what change is realistic, and then ask a simple question: is that change worth that scar for you.
Caution is warranted in several situations. Where laxity is mild, the scar cost can exceed the benefit, and it is often more intelligent to do less — or nothing — than to earn a scar that becomes the main story. Where weight is unstable, the envelope is still changing and a stable contour is harder to design. Where expectations include scarlessness, perfect symmetry, or a dramatic template change, the constraint is not technical but one of expectation. And where the motivation is perfection-chasing rather than a stable, lived complaint, revision pathways become more likely and satisfaction less predictable.
In those settings the safest plan may be to wait, to choose a smaller intervention with modest expectations, or to do nothing. Those are not weak recommendations. They are protective ones — non-intervention is a legitimate clinical endpoint when the trade-off is not fair.
Symmetry deserves its own sentence. Arms are not identical at baseline and healing is not identical from side to side. Symmetry is a goal, not a promise; the purpose of surgery is refinement and proportion rather than engineered sameness.
Recovery, and why it varies
There is a typical course, but it is not identical for everyone. Swelling and firmness settle in stages, and the arm can feel firm and tight early on.
Recovery is a sequence, not a single date.
-
Early phase
Swelling, firmness and tightness
Movement and daily use can temporarily increase swelling, which can make the contour look uneven at this stage.
-
Settling phase
Swelling resolves in stages
The arms can look uneven at times while the tissues settle. Some people feel functional quickly; others take longer, and that variability is normal.
-
Maturation phase
Scar maturation, measured in months
Scar maturation is a long process that evolves over months rather than weeks. The goal is progressive settling rather than immediate perfection.
Early is not final. If a fixed look is needed by a fixed date, that constraint belongs in the conversation before surgery, because biology does not behave like a calendar.
What should be weighed in the decision?
The risks that matter here are the ones that shape the plan and determine how much correction is justified. None of them are abstract; they are the constraints on the operation itself.
- Trade-off: meaningful skin removal requires a scar. Placement and tension can be planned, but scar biology varies — some scars mature quietly, others widen or pigment more noticeably.
- Trade-off: wound healing variability, infection, fluid collections, scar widening, contour irregularity, asymmetry and sensation changes along the incision line all belong in the decision.
- Limitation: symmetry is a goal, not a promise. Arms differ at baseline and heal differently from side to side.
- Limitation: a very short scar cannot remove enough skin to change the silhouette when laxity extends toward the elbow.
- Limitation: over-tightening can make the contour look pulled and can worsen scar quality — the arm has to look normal in motion, not only when posed.
- Alternative: where fat is the dominant driver and skin recoil is reasonable, liposuction may deliver a cleaner improvement for a smaller footprint.
- Alternative: where laxity is mild, weight is unstable, or the scar burden clearly exceeds the likely benefit, waiting, a smaller intervention or no surgery is the more honest plan.
Revision brachioplasty
Revision is different from a first-time arm lift, not because someone tries harder, but because the tissue has changed. Scar planes alter how tissue glides, elasticity is often reduced, and blood supply patterns can be less forgiving. That narrows the safe range of correction and reduces predictability.
The right way to think about revision is mechanism definition rather than touch-up: is the problem residual skin in one segment, a contour irregularity, or scar behaviour that has become unacceptable. Timing matters too, because early healing can mimic a problem. In revision planning I prefer targeted goals, conservative tension, and the acceptance that better is often safer than perfect. Sometimes improvement is appropriate. Sometimes escalation is not.
How long the result lasts
Many arm lift results can be long-lasting, but they are not immune to biology. Ageing continues, skin elasticity changes, and weight fluctuation can alter both the envelope and the distribution of volume. I avoid permanent as a promise; the more honest concept is stability under stable conditions.
Where weight remains stable and tissue behaviour is favourable, results often remain satisfying for years. Where the body changes significantly, the arm contour changes with it. The aim is not an arm that ignores time. It is a refined contour that stays proportionate and believable as the body continues to live.
How do I know whether I need an arm lift or just arm liposuction?
This is anatomy-based, not preference-based. The key question is what limits the silhouette. If the arm looks heavy primarily because of fat thickness and the skin has reasonable recoil, liposuction can sometimes deliver a clean improvement. If the main limitation is skin laxity, liposuction does not reliably tighten the envelope — removing fat can leave the same loose envelope with less internal support, and the arm can look more lax. Mixed patterns are common after weight changes and with age-related loss of recoil, and there the plan has to be conservative, because aggressive contouring can create irregularities.
If an arm lift removes skin, why doesn’t everyone with heavy arms need one?
Because not every arm complaint is a skin problem. Many people interpret localised fullness as loose skin when the dominant driver is volume. Others have mild laxity, but the improvement available from excision would be small relative to the scar trade-off. An arm lift is an excision procedure, and the price of meaningful skin removal is a longer incision. If the arm is within normal variation and the concern is modest, it is often more intelligent to do less, or nothing, rather than earn a scar that becomes the main story.
Where are the scars placed, and what determines how visible they become?
Scars exist because skin removal requires an incision. Placement is planned to be as discreet as the anatomy allows, but visibility is heavily influenced by tension and by individual biology. High-tension closure raises the risk of widening; thin or fragile skin makes scar behaviour less predictable; pigmentation tendencies vary between individuals and skin types. I can control incision placement and tension strategy. I cannot control scar biology by agreement. Scars usually mature and fade, but they do not become imaginary, and the trade-off should be accepted in advance rather than hoped away.
Can it be done with a small scar only?
Sometimes, but only in a specific anatomy, and the honest limitation is geography. If laxity extends along the inner arm toward the elbow, a very short scar cannot remove enough skin to change the silhouette meaningfully. When a mini scar is requested within a larger laxity pattern, the outcome tends to be either under-correction or a scar under tension that heals poorly. The correct question is not how short the scar can be, but what footprint is justified by the degree and location of laxity. Where laxity is mild and localised, a limited approach may be reasonable.
When is an arm lift not the right answer?
When expectations include scarlessness, perfect symmetry, or a dramatic template change. When weight is unstable, because contour design requires a stable baseline and durability becomes less predictable if the baseline is moving. When laxity is mild and the scar burden clearly exceeds the likely benefit. And when the motivation is perfection-chasing rather than a stable, lived complaint, since revision pathways then become more likely and satisfaction less predictable. In these situations the safest plan may be to wait, to choose a smaller intervention with modest expectations, or to do nothing.
Can an arm lift look unnatural or operated?
Yes, and the most common reason is over-tightening. The arm has to look normal when it moves, not only when it is posed. Excessive tension can make the contour look pulled and can increase scar tension, which may worsen scar quality. The other cause is disproportion: reducing the arms considerably while the torso is untreated creates a visual mismatch. My bias is toward controlled refinement and proportion. A quiet result is usually a better result, because it reads as normal anatomy rather than as an edited body.
What does recovery feel like, and why does it vary?
There is a typical course, but it is not identical for everyone. Swelling settles in stages and the arm can feel firm and tight early on. Movement and daily use can temporarily increase swelling, which makes the contour look uneven in the early phase. Scar maturation is a long process that evolves over months. Some people feel functional quickly, others take longer. Early is not final — and if a fixed outcome is needed by a fixed date, that constraint should be discussed before surgery, because healing does not follow a calendar precisely.
What are the main risks you take seriously?
The ones that shape the plan and influence the trade-off: wound healing variability, infection, fluid collections, scar widening, contour irregularity, asymmetry, and sensation changes along the incision line. None of these are abstract. They are the constraints that determine how aggressive the correction can be and what scar footprint is justified. I do not minimise them in language. The purpose is not to frighten anyone but to plan honestly, so that the procedure remains appropriate and the expectations remain realistic.
What if I have already had arm surgery and want a revision?
Revision arms behave differently, because the tissue has changed. Scar planes alter glide, elasticity is often reduced, and blood supply patterns can be less forgiving, which narrows the safe range of correction and reduces predictability. The right way to think about it is mechanism definition rather than touch-up: is the problem residual skin in a segment, a contour irregularity, or scar behaviour that has become unacceptable. Timing matters too, since early healing can mimic a problem. I prefer targeted goals, conservative tension, and the acceptance that better is often safer than perfect.
How long do the results last?
Many results can be long-lasting, but they are not immune to biology. Ageing continues, skin elasticity changes, and weight fluctuations can change both the envelope and the distribution of volume. I avoid permanent as a promise; the more honest concept is stability under stable conditions. If weight remains stable and tissue behaviour is favourable, results often remain satisfying for years. If the body changes significantly, the arm contour can change too. The aim is a refined contour that stays proportionate and believable as the body continues to live.



